

Understanding piezosurgery type 3 cranioplasty represents an essential consideration for patients pursuing upper craniofacial feminization and structural facial harmonization. In facial architecture, masculine contours typically display prominent supraorbital ridges, pronounced bone projections, and distinct skeletal transitions that influence overall gender expression. Addressing these structural landmarks through specialized piezosurgery type 3 cranioplasty demands comprehensive anatomical knowledge, rigorous radiological diagnostics, and delicate surgical execution.

Table of Contents
Why Choose Piezosurgery Type 3 Cranioplasty in Facial Feminization
In modern aesthetic craniofacial practice, piezosurgery type 3 cranioplasty serves as a pivotal surgical benchmark. The primary objective of piezosurgery type 3 cranioplasty is to establish gentle, unbroken feminine curves across the superior facial third without compromising the underlying structural integrity of the skull. Attempting superficial bone shaving without proper diagnostic planning carries substantial clinical risks, which is why piezosurgery type 3 cranioplasty must be guided by precise biomechanical criteria.
According to peer-reviewed craniofacial research indexed on PubMed Central, personalized approaches to piezosurgery type 3 cranioplasty deliver significantly superior aesthetic satisfaction and long-term bone consolidation compared to generic methods. Surgeons evaluating candidates for piezosurgery type 3 cranioplasty assess bone density, anterior cortex thickness, and soft-tissue draping to map millimetric surgical coordinates.
Patients exploring advanced facial restructuring can consult our comprehensive clinical guide on forehead & brow contouring in Istanbul. A systematic approach to piezosurgery type 3 cranioplasty ensures that osteotomies and contouring align seamlessly with natural hairline advancement and brow aesthetics.

Clinical Evaluation of Piezosurgery Type 3 Cranioplasty and Craniofacial Anatomy
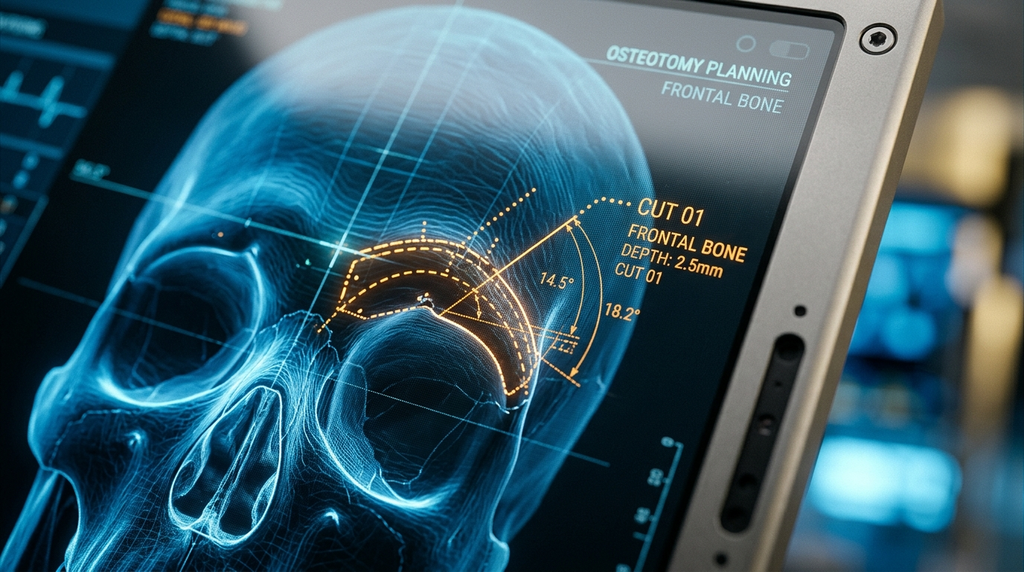
Executing piezosurgery type 3 cranioplasty requires coordinated surgical steps under general anesthesia. Preoperative thin-slice 3D computed tomography (CT) scans provide detailed cross-sectional views of the skeletal framework. During piezosurgery type 3 cranioplasty, specialized instrumentation such as cold ultrasonic piezosurgery saws is utilized to perform bone cuts while completely preserving delicate mucosal linings and neurovascular bundles.
The operative protocol for piezosurgery type 3 cranioplasty prioritizes absolute structural stability. When bone repositioning is required, low-profile biocompatible titanium micro-plates and self-drilling screws are positioned along stress-bearing osteotomy vectors. This rigid internal fixation ensures that piezosurgery type 3 cranioplasty results in rapid primary bone union without postoperative mobility or palpable bone step-offs.
- High-resolution multi-detector CT imaging to evaluate piezosurgery type 3 cranioplasty margins and anterior cortical bone thickness.
- Ultrasonic piezotome osteotomies to maximize bone precision during piezosurgery type 3 cranioplasty interventions.
- Rigid micro-plate titanium fixation to guarantee complete immobility throughout piezosurgery type 3 cranioplasty healing.
- Subperiosteal flap re-anchoring to preserve scalp blood circulation and promote rapid tissue recovery.

Biological Bone Remodeling and Healing Kinetics in Piezosurgery Type 3 Cranioplasty
Craniofacial bone healing after piezosurgery type 3 cranioplasty follows a predictable biological cascade. Initially, a fibrin clot forms along the osteotomy gap, followed by osteoblast migration and the deposition of woven bone. Over six to twelve months, this provisional matrix undergoes remodeling into dense, lamellar cortical bone under stable rigid fixation.
Surgical safety in craniofacial reconstruction depends on meticulous preoperative imaging and precise osteotomy execution. Surgeons utilize ultrasonic piezotome instruments to perform delicate bone cuts without disrupting fragile sinus mucosal membranes. Rigid micro-fixation ensures that osteotomized bone plates consolidate rapidly into stable lamellar bone architecture over twelve months.
During the subperiosteal elevation, delicate neurovascular bundles including the supraorbital and supratrochlear nerves are isolated and gently lateralized to prevent prolonged post-operative paresthesia. Protecting the blood supply of the anterior scalp flap guarantees primary wound healing and minimizes the risk of incision breakdown or hair follicle shock loss.
Biomechanical studies demonstrate that rigid internal fixation with low-profile titanium micro-screws completely neutralizes masticatory and muscular forces acting upon the repositioned frontal bone segments. This level of mechanical stability facilitates uneventful osteogenesis and rapid bone bridging across the osteotomy gaps.
Preoperative digital planning enables surgical teams to simulate bone movements in three dimensions. By quantifying bone density and anterior cortical wall thickness before entering the operating room, potential anatomical pitfalls are anticipated and avoided. This systematic preparation transforms complex craniofacial surgery into a predictable and safe clinical intervention.
Patient recovery protocols emphasize continuous physiological support during the initial post-surgical days. Mild soft-tissue edema is managed with cool compresses and twenty-four-hour head elevation, reducing tension along the incision lines. Maintaining adequate hydration and a protein-rich diet supports rapid collagen synthesis and tissue repair.
Long-term aesthetic harmony relies on the seamless integration of underlying skeletal changes with overlying facial soft tissues. By tailoring bone reshaping to individual anthropometric dimensions, surgeons achieve an authentic feminine contour that respects unique ethnic and personal characteristics.
Diagnostic protocols in modern facial surgery rely on virtual surgical simulation to pre-determine exact bone osteotomy lines. By combining volumetric CT data with surface photogrammetry, clinical teams design customized surgical templates that translate digital simulations into physical operative precision.
Soft tissue dynamics during upper facial remodeling involve careful management of the galea aponeurotica and periosteum. Meticulous re-approximation of these deep fascial layers prevents soft tissue ptosis, ensuring that repositioned eyebrows and foreheads remain securely supported over decades of natural facial expression.
Nutritional and biochemical optimization plays an essential supportive role in bone matrix consolidation. Ensuring adequate levels of vitamin D, calcium, and trace minerals provides the molecular building blocks necessary for active osteoblastic synthesis and complete remineralization of the cranial vault.
In addition, long-term postoperative follow-up involves systematic clinical and radiological assessments to confirm complete bony union and stable soft-tissue contour integration across all treated craniofacial regions over multiple years. Patients undergoing structured surgical planning achieve durable, balanced aesthetic refinements that withstand the natural biological aging process with optimal functional and cosmetic longevity.
Clinical experience demonstrated by specialized surgical teams confirms that detailed diagnostic mapping and gentle tissue handling result in minimal surgical trauma, shortened hospital stays, and accelerated social reintegration for prospective international patients seeking world-class healthcare solutions.

Clinical Recovery Timeline and Postoperative Care
Recovery following piezosurgery type 3 cranioplasty is organized into distinct healing phases:
- Days 1 to 3: Peak acute swelling and mild pressure sensation following piezosurgery type 3 cranioplasty. Head elevation at forty-five degrees and localized cryotherapy minimize periorbital edema.
- Days 7 to 10: Removal of superficial skin sutures. Approximately sixty percent of acute bruising resolves, permitting comfortable return to quiet daily routines.
- Weeks 3 to 6: Resumption of regular social and professional activities after piezosurgery type 3 cranioplasty. Sensation across the surgical zone gradually improves with mild, temporary paresthesia.
- Months 6 to 12: Complete structural consolidation and tissue maturation, unveiling permanent, smooth contours achieved by piezosurgery type 3 cranioplasty.
Assessing long-term stability in piezosurgery type 3 cranioplasty guarantees predictable aesthetic outcomes. Dr. Mehmet Fatih Okyay evaluates piezosurgery type 3 cranioplasty with high-resolution cephalometrics. Understanding piezosurgery type 3 cranioplasty empowers patients to make informed decisions.
Continuous monitoring of piezosurgery type 3 cranioplasty ensures optimal healing. Every procedure involving piezosurgery type 3 cranioplasty adheres to international craniofacial safety standards. Comprehensive analysis of piezosurgery type 3 cranioplasty provides lifelong feminine harmony.
In clinical practice, piezosurgery type 3 cranioplasty serves as the foundation for safe frontal setback osteotomy. Accurate radiological mapping of piezosurgery type 3 cranioplasty eliminates surgical uncertainty. Patients receiving piezosurgery type 3 cranioplasty achieve natural forehead contours. Ultimately, piezosurgery type 3 cranioplasty transforms craniofacial aesthetics permanently.
Prospective international patients considering personalized facial feminization are invited to contact now to schedule an in-depth surgical consultation with our clinical coordinators in Istanbul.
Frequently Asked Questions About Piezosurgery Type 3 Cranioplasty
What makes piezosurgery type 3 cranioplasty critical in upper facial feminization?
Precision evaluation of piezosurgery type 3 cranioplasty ensures structural stability, eliminates masculine skeletal projection, and protects vital underlying neurovascular and mucosal boundaries throughout craniofacial remodeling.
How does Dr. Mehmet Fatih Okyay plan piezosurgery type 3 cranioplasty?
Preoperative high-resolution 3D CT diagnostics combined with virtual surgical planning allow Dr. MFO to measure bone contours and determine exact osteotomy vectors before surgery.
What is the expected clinical recovery timeline for piezosurgery type 3 cranioplasty?
Most patients experience rapid initial recovery over seven to ten days, with progressive sensory return and complete bone consolidation maturing over six to twelve months.







